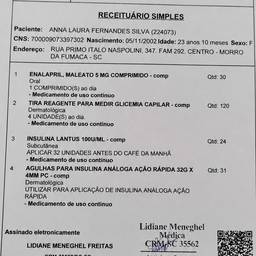
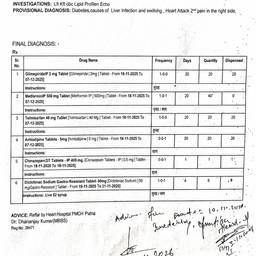
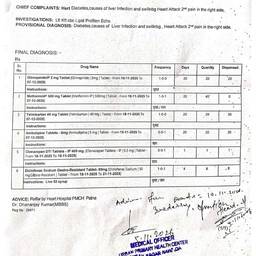
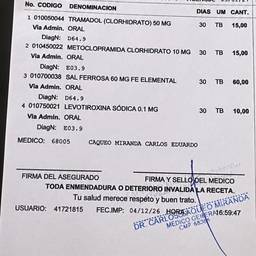
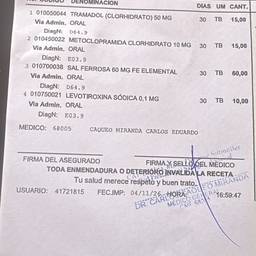
Bearbeitung des medizinischen Rezeptformulars


medizinisches rezept mit ki bearbeitenpatientendaten zu einem medizinischen formular ki hinzufügenleere felder in einem medizinischen formular ki ausfüllen
Prompt
Edit the medical prescription form. Fill in the fields as follows: - Paciente: 77145650 FIGARI IRIGOYEN NICOLE ARIANA - Fecha de atención: 09/11/2026 - Identificación: 77145650 - Sexo: Femenino - Fecha de nacimiento: 30/07/2000 - Edad: (26 años) - Email: Rochifigari@hotmail.com - Fecha registro: 07/04/2026 - Contratante: SANITAS Keep the rest of the form exactly the same, including the hospital header, medications (omeprazole, domperidone), and instructions. Only fill in the blank fields with the provided text.
Mehr davon